Obstructive urolithiasis is a common emergency for small ruminants. The post Diagnosis and Management of Obstructive Urolithiasis in Small Ruminants appeared first on Today's Veterinary Practice.
Obstructive urolithiasis is a common emergent condition affecting small ruminants. A complete urinary obstruction can lead to life-threatening electrolyte imbalances as well as potentially permanent renal damage and urinary bladder or urethral rupture. Obstructive urolithiasis can be diagnosed by the collection of a thorough history, physical examination, and abdominal imaging. The type of urolith and location of obstruction determine the treatment options and prognosis. The treatment options vary and often include a combination of medical management and surgical procedures.
Take-Home Points
- Risk factors include anatomy, urine pH, water intake, diet, and possibly breed; however, small ruminants may develop urolithiasis despite having no notable risk factors.
- Common clinical signs include tail flagging, vocalizing, flank watching, standing in a stretched-out stance, a tense or distended abdomen, inability to settle or stand, and lethargy.
- Ultrasonography is the most useful diagnostic tool for confirming obstructive urolithiasis. Radiography is useful for determining the type of urolith and location.
- Treatment often includes a combination of medical management and surgical procedures; however, obstruction recurrence is common. Euthanasia is an appropriate and humane option for these patients.
Urolithiasis is a common condition affecting small ruminants, one that is frequently encountered with the increase of small ruminants as companion animals. Obstructive urolithiasis is an emergency, and swift diagnosis and treatment are critical. The ability to identify at-risk ruminants enables closer monitoring, which can lead to faster interventions. Furthermore, an understanding of the various risk factors associated with urolithiasis can facilitate preventive measures. Although multiple risk factors have been identified, a small ruminant may develop urolithiasis despite having no notable risk factors.
History
The collection of a thorough history with assessment of diet, recent stressors, and water intake is essential to identifying any potential risk factors for obstruction. A client may report that an animal is straining to urinate, dribbling urine, straining to defecate, or appearing constipated. Additional common clinical signs include tail flagging, vocalizing, flank watching, standing in a stretched-out stance, tense abdomen, and being unable to settle. A severely affected animal may be lethargic or unable to stand, or their abdomen may be distended, which may be suggestive of severe electrolyte abnormalities or urinary bladder rupture, respectively. An animal with clinical signs of less than 24 hours’ duration is more likely to have a positive outcome; therefore, establishing an accurate timeline of clinical signs is a determining factor of prognosis.1
Risk Factors
Anatomy
The anatomy of the urinary tract of a male small ruminant is a predisposing factor for obstruction. The male urethra is significantly longer than the female urethra. Common locations for obstruction are the 2 curves of the sigmoid flexure and urethral process at the distal tip of the penis, all of which have a narrowed urethral diameter. Castrated males are over-represented as the most common signalment affected by obstructive urolithiasis. Early castration may be a contributing factor to urolith development because that may lead to a narrower urethral lumen.2
Alkaline pH
The normal pH of urine from a small ruminant is alkaline, which is a risk factor for urolith formation. That pH is a result of their primarily forage diets, which are high in potassium. Commonly occurring uroliths, such as magnesium ammonium phosphate (i.e., struvite) and calcium carbonate, form in alkaline urine.
Water Intake
Decreased water intake leads to increased urine concentration, which causes supersaturation of crystals in urine and enables urolith formation. Changes in weather, travel, stress, and decreased water access are common reasons for decreased water intake.
Diet
Some dietary factors have been shown to have an association with certain types of urolith formation. For example, diets high in calcium (e.g., alfalfa) are associated with calcium carbonate urolith formation. Primarily grain diets have been associated with phosphatic urolith formation (e.g., magnesium ammonium phosphate, amorphous magnesium calcium phosphate), which is attributed to abnormalities in the calcium-to-phosphorus ratio.3,4 Diets high in oxalates (e.g., certain clovers) can contribute to calcium oxalate urolith formation. Diets grown in soils with high silica levels can lead to silicate urolith formation.
Other Factors
Urolithiasis can occur at any age. Nigerian Dwarf and Pygmy goat breeds have been reported to be over-represented breeds diagnosed with urolithiasis. However, that association may be a result of the increased likelihood for these breeds to be pets and, thus, clients are more likely to pursue veterinary care.5
Physical Examination
A thorough physical examination is an important diagnostic for any disease but especially for obstructive urolithiasis. Tachypnea and tachycardia are often observed due to stress and/or pain. Bradycardia or bradyarrhythmia may be an indication of hyperkalemia, which is a severe sequela of obstructive urolithiasis and requires immediate intervention. Animals may be painful on palpation of their abdomen and prepuce; however, this should be interpreted with caution, as small ruminants are often not accustomed to abdominal palpation and may be reactive from fear. Additional abnormal findings may include a urethral pulse on rectal exam or crystalline debris on the hair surrounding the prepuce. Ventral abdominal swelling or edema can be an indication of urethral rupture.
Diagnostics
Ultrasonography
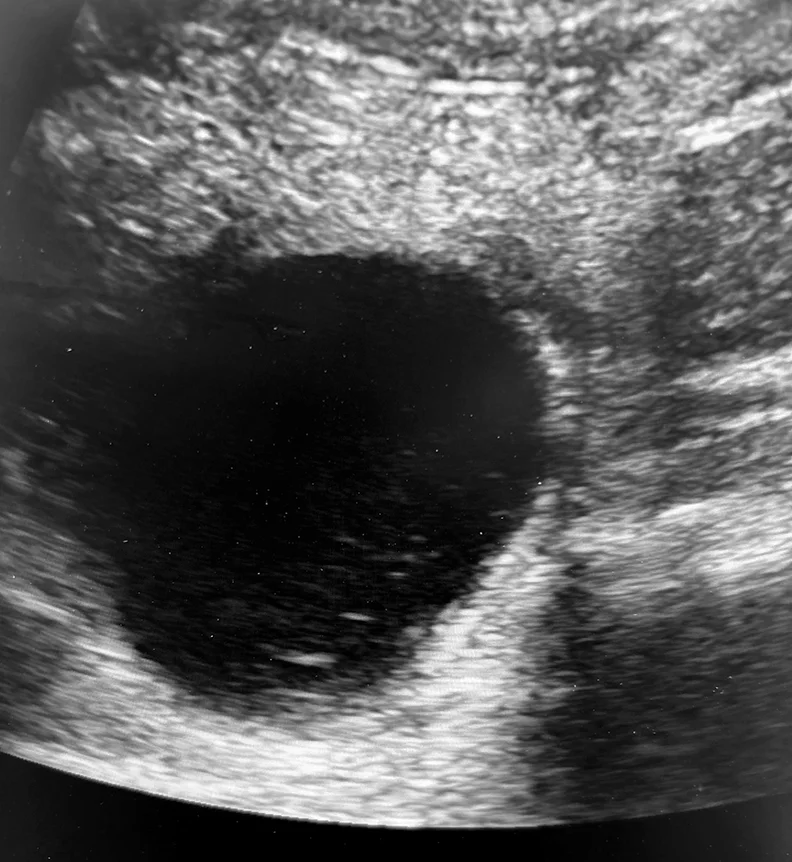
Ultrasonography is the most useful diagnostic for confirming obstructive urolithiasis. A large, round, turgid urinary bladder is consistent with urinary obstruction (FIGURE 1). A bladder diameter greater than 8 cm is consistent with obstruction for large-breed goats such as Boer or Nubian. A bladder diameter greater than 6 cm is consistent with obstruction for smaller breeds such as Nigerian Dwarf or Pygmy. However, due to the range of bladder sizes of goats, any bladder—regardless of diameter—that is round and turgid on ultrasonography is indicative of urinary obstruction.
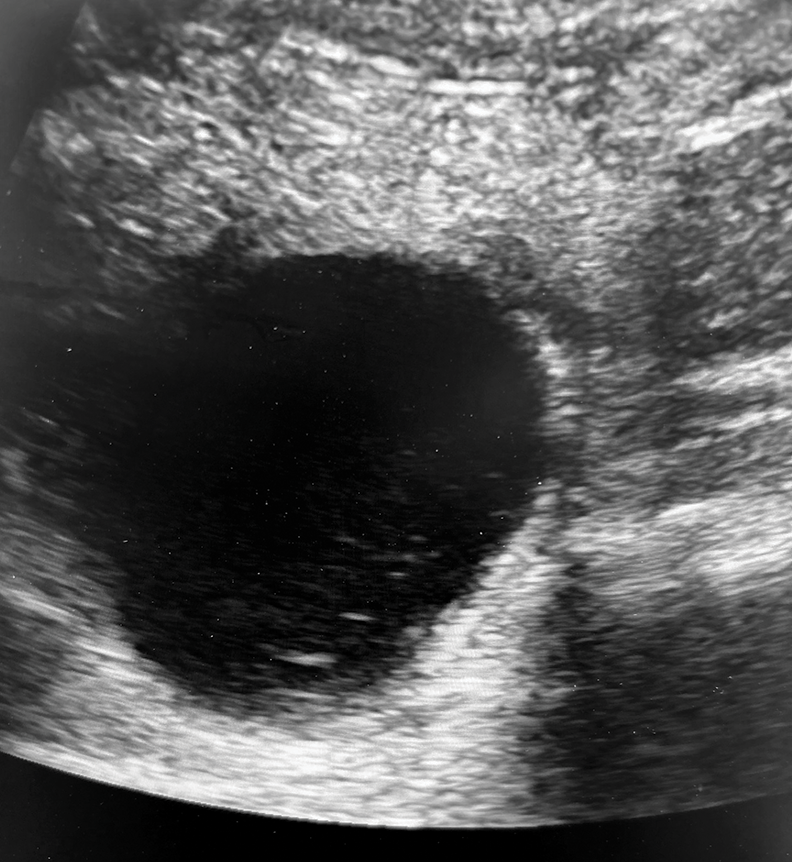
Figure 1. Ultrasonography image of a round, turgid urinary bladder, indicative of urinary obstruction.
Unlike uroliths in small animals, uroliths in small ruminants are often not detectable by ultrasonography. However, a hyperechoic, “snow globe” appearance of urine is an indication of struvite crystalluria.
Ultrasonography is also important for assessing the kidneys, as prolonged obstruction can lead to hydronephrosis or rupture of the capsule, which affects prognosis. The kidneys in small ruminants are visible from the right paralumbar fossa.
Ultrasonography of the urethra can be challenging, especially in larger or heavily conditioned animals. Subcutaneous edema or fluid around the urethra can be an indication of urethral rupture. Occasionally, ultrasonography can be used to identify the location of uroliths within the lumen.
Free fluid within the abdomen is consistent with uroperitoneum. A small amount of urine commonly leaks through an inflamed and turgid bladder wall. However, if no defined bladder is visualized, urinary bladder rupture should be suspected; emergency surgery is indicated. If surgery is not an option, euthanasia is recommended.
Radiography
Radiography is an extremely useful diagnostic tool for determining the suspected type of urolith and location. Radiographic views should include the bladder and entire urethra. Although a definitive diagnosis of the type of urolith requires laboratory analysis, radiographs can suggest the type of urolith. Rounded uroliths of mineral opacity within the bladder or urethra are suggestive of calcium-based uroliths (FIGURE 2). Struvite or other phosphatic uroliths are not often visible on radiographs of larger patients, but they may be seen in smaller patients.6 This is an important distinction because calcium carbonate uroliths necessitate surgical removal.
Contrast radiography can be helpful if uroliths are not readily detected by radiography or urethral stricture is suspected.7 Contrast studies may also be helpful for identifying sites of urethral rupture.
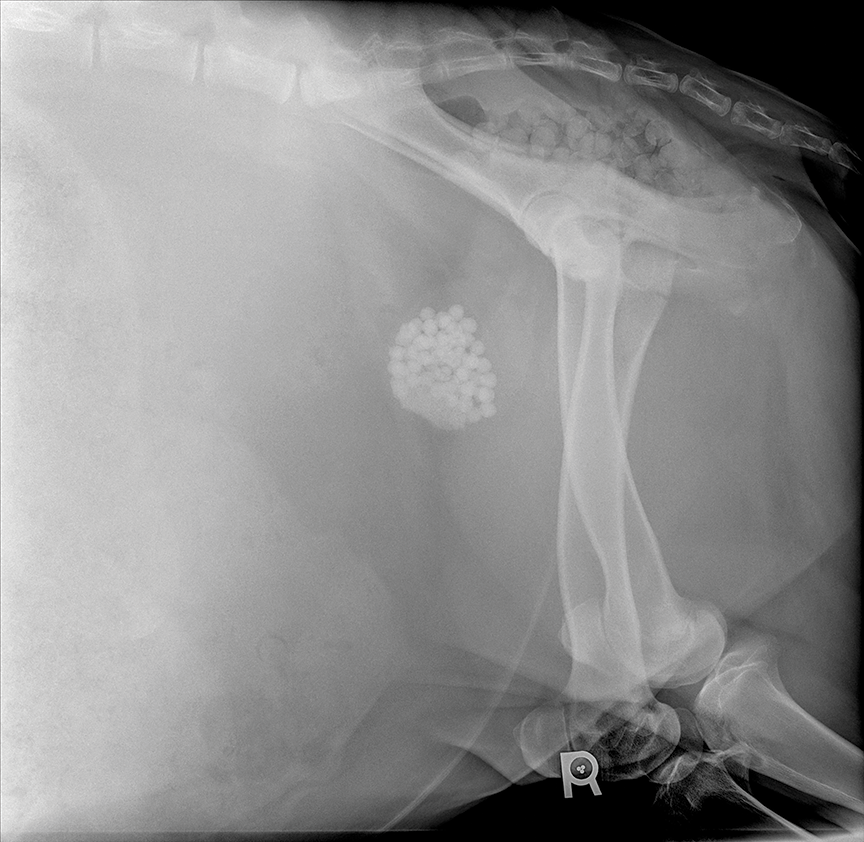
Figure 2. Radiograph showing radiopaque uroliths within the urinary bladder of a goat. The rounded mineral opacities are consistent with calcium carbonate uroliths.
Bloodwork
A CBC and serum biochemical profile can range from normal to severely altered depending on the duration of obstruction. Elevations in packed cell volume and total solids, consistent with dehydration and hemoconcentration, are common. Hyperkalemia can arise from prolonged obstruction or urinary bladder rupture and lead to life-threatening bradyarrhythmia. Elevated creatinine is frequently observed and may be attributed to a combination of pre- and postrenal causes. Azotemia should be closely monitored following treatment for urolithiasis, as persistently elevated creatinine may be reflective of permanent renal damage and can influence prognosis. Systemic lactate may also be elevated from dehydration and decreased perfusion. Abnormal packed cell volume, severely increased serum creatinine concentration, and increased creatine kinase activity have been associated with increased risk for nonsurvival.1
Treatment
Treatment options are determined by the condition of the patient, type of urolith, intended use of the patient, and other external factors. Successful treatment often requires a combination of medical and surgical techniques. Initial treatment consists of relieving the obstruction by either removing the offending urolith or creating a temporary urinary diversion, stabilizing electrolyte abnormalities, and eventually removing the remaining uroliths. Referral for more extensive surgical options may not be available in all geographic areas, and the costs associated with surgery or prolonged medical treatment can be limiting factors.
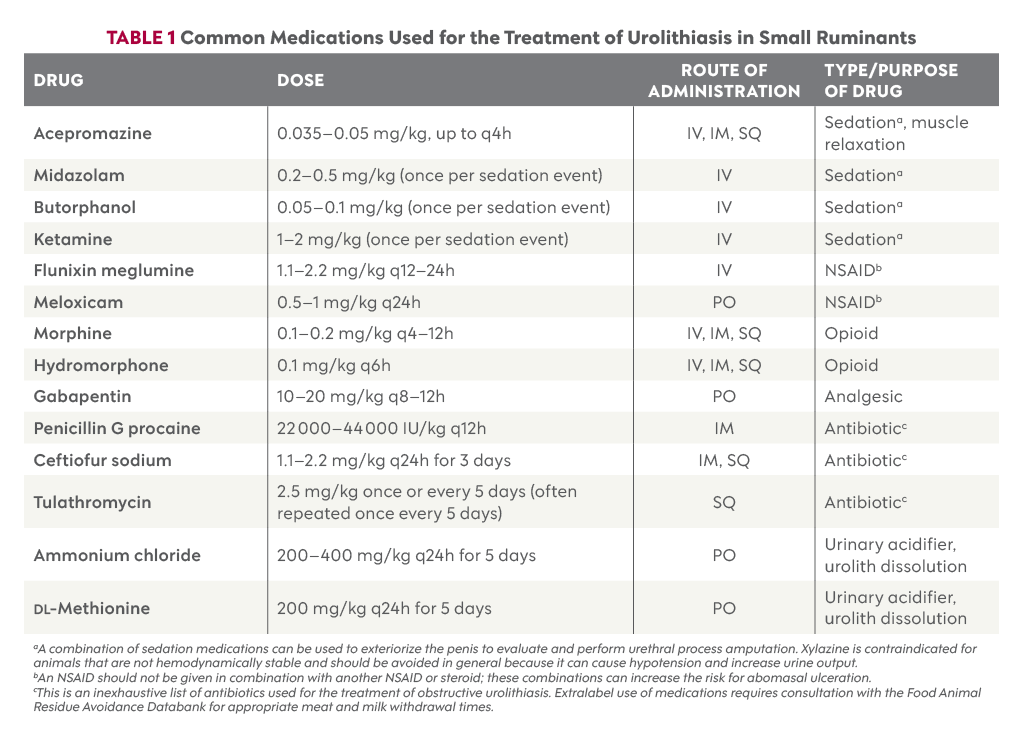
Extralabel use of medications for small ruminants requires consultation with the Food Animal Residue Avoidance Databank (FARAD) for appropriate meat and milk withdrawal times. This includes all sedatives, muscle relaxants, pain medications, and antibiotics (TABLE 1).
Medical Management
Urethral Process Amputation
One of the most common sites for urolith obstruction is the urethral process, or the “pizzle,” due to its distal location and narrow diameter (FIGURE 3). Urethral process amputation is both a treatment and diagnostic and should be done for all cases of obstructive urolithiasis.
Sedation is required for exteriorization. Placing the animal on their rump or in lateral recumbency with their hind limbs pulled cranially helps facilitate straightening the sigmoid flexure and exteriorizing the penis. Animals that were castrated at a young age may have persistent adhesions. Once visualized, the distal portion of the urethra can be palpated for any uroliths or crystals and amputated proximally at an oblique angle to maximize the diameter of the opening. Caution should be used to not cut the penis itself as that can cause pain and excessive bleeding. Following amputation, an 8- or 10-Fr polypropylene catheter can be passed retrograde to assess for obstruction and gently flush crystals or debris from the urethra. Passing this catheter completely to the bladder will not be possible in most animals because the catheter will be diverted into the urethral recess.
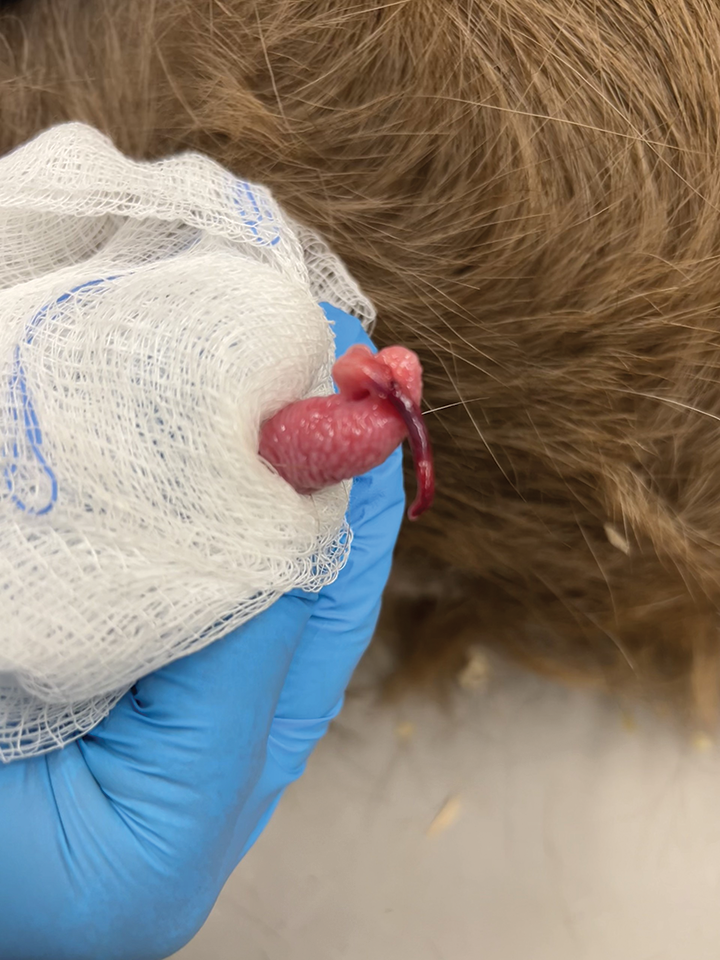
Figure 3. A necrotic urethral process, and dilated urethra proximally, after prolonged obstruction.
Percutaneous Transabdominal Catheter Placement
A temporary percutaneous transabdominal catheter can be used before anesthesia for a surgical procedure or as a component of medical management.8 If an animal does not begin to urinate after urethral process amputation, or if an animal requires immediate stabilization before urethral process amputation, a transabdominal catheter can be placed for temporary urinary diversion. This should be done with ultrasound guidance under sedation.
Types of percutaneous transabdominal catheters include Bonanno and pigtail catheters in addition to Foley catheters that can be placed using a metal trocar. Although these catheters may only maintain patency for a short period of time, with 1 study describing a range of 1 to 4 days, they can be extremely useful for providing time to dissolve struvite uroliths or resolve urethral inflammation and spasms following urethral process amputation.8
Complications commonly seen with these catheters include blockage and migration out of the bladder. Given these limitations, patient selection is important. Heavily conditioned or large-framed patients, as well as patients with significant debris in the bladder (e.g., large fibrin, blood clots) or indissoluble urolith types, are less ideal for this type of catheter placement.
Cystocentesis
Cystocentesis has limited utility for the management of urolithiasis in small ruminants. Decompressive cystocentesis has temporary effects and can increase the risk for uroabdomen yet may be necessary if surgical intervention is delayed. Infusion of Walpole’s solution into the bladder is a described technique for dissolution of struvite uroliths but should be considered a salvage procedure before euthanasia, as leakage of the solution causes inflammation and peritonitis.9
Stabilization
Stabilization of the patient following removal of the obstruction or temporary urinary diversion is critical and should aim to resolve dehydration, electrolyte derangements, and metabolic disturbances.
Urethral spasm associated with obstruction and urethral inflammation is painful and may benefit from a muscle relaxant (e.g., acepromazine). NSAIDs (e.g., flunixin meglumine, meloxicam) should be administered after azotemia has been addressed to control pain and inflammation. Opioids (e.g., morphine, hydromorphone) should be considered for patients with severe pain or when NSAIDs are contraindicated. See TABLE 1 for dosages.
Dissolution
Of all the types of uroliths that are common in small ruminants, only struvite uroliths are susceptible to dissolution by acidifying urine (i.e., lowering the pH). The success of dissolution depends on the size and number of uroliths and response to therapy. Options for acidification include direct infusion of acidifying solutions into the bladder or oral acidification medications. If a temporary percutaneous transabdominal catheter has been placed, direct infusion of Walpole’s solution with ultrasound guidance can quickly lower urine pH. This is preferable to cystocentesis with Walpole’s solution because the catheter enables the solution to be safely drained from the bladder following infusion. Oral acidification medication options include ammonium chloride and ᴅʟ-methionine (TABLE 1).10
Urine pH should be monitored daily during use of these medications to confirm efficacy. The goal is to decrease urine pH below 6.5 for 4 to 5 days to enable dissolution of uroliths or crystals. Pulse dosing—during which ammonium chloride is administered for 3 days, discontinued for 4 days, and repeated 2 to 3 times—can be useful for patients requiring prolonged administration for complete resolution.11
Long-term routine use of urine acidifiers is not recommended because an animal will develop a tolerance. In addition, prolonged use of ammonium chloride has been shown to increase calcium excretion in urine, which may predispose to the formation of calcium-containing uroliths.12
Surgical Management
Surgery is indicated for patients with insoluble uroliths, soluble uroliths that have not responded to medical therapy, or complications such as urethral rupture.
Tube Cystotomy
Tube cystostomy enables a secure, longer-term outlet for urinary diversion than temporary transabdominal catheter placement as well as removal of uroliths from the bladder. This surgery is performed under general anesthesia with the patient in dorsal recumbency and through a ventral midline approach. During cystotomy, uroliths can be removed and inflammatory debris can be lavaged. Additionally, normograde or retrograde flushing of the urethra can be performed intraoperatively to remove uroliths. Urethrotomy may still be required for some patients. A Foley catheter (8- to 28-Fr depending on patient size) is then placed through a paramedian incision and secured in the bladder by a purse-string suture. The Foley is secured against the abdominal wall and sutured to the skin by a purse-string and finger-trap. The Foley stays in place for 10 to 14 days. After the allotted healing time, the Foley can be occluded for increasing amounts of time and the patient monitored for appropriate urination. If the patient is urinating appropriately after the Foley has been occluded for 24 hours, the Foley can be removed by removing the skin sutures and deflating the balloon. The adhesions formed between the bladder and body wall prevent uroabdomen formation following catheter removal.13
If an animal does not begin to urinate appropriately after occlusion of the Foley catheter, reassessment is required. Multiple factors—including persistent urethral pain or inflammation, urethral stricture, or the presence of additional uroliths—may be contributing. Radiography with or without contrast and exteriorization of the penis to assess for urethral process stricture are indicated and should be repeated. For some patients, the addition of a muscle relaxant and NSAID for a few days before and during Foley catheter occlusion can be helpful for controlling pain and enabling urination. If a repeated Foley occlusion challenge fails, then a discussion about salvage procedures or euthanasia is recommended.
Potential complications can include premature removal of the Foley; thus, individual housing with close monitoring is recommended. Due to the risk for ascending infection or cystitis while the Foley is in place, broad-spectrum antibiotics may be recommended.14 In addition, the bladder may remain adhered to the body wall; these adhesions may complicate any future abdominal surgery.
A minimally invasive modified tube cystotomy technique has been described. With this technique, a patient is sedated and a suprapubic catheter introducer is used to insert a Foley catheter through a small left flank incision. Discretion with patient selection for this technique is recommended due to increased risk for complications with larger and heavily conditioned animals.15
Urethrotomy
Urethrotomy, or incision into the urethra to remove a urolith, may be necessary if flushing of the urethra is not successful. This surgery is often performed concurrently with a tube cystotomy. Potential surgical complications include dehiscence, infection, stricture, and reobstruction.16
Perineal Urethrostomy
Perineal urethrostomy may be considered if a patient has experienced multiple repeated obstructions or the distal penile urethra has ruptured. A patient is sedated or placed under general anesthesia, and a stoma is created to permanently divert urine proximal to the obstruction site. Multiple different approaches have been described, including a standard perineal urethrostomy and modified perineal urethrostomy. The modified technique involves a more extensive dissection of penile tissue to spatulate a larger area of urethra, which has been suggested to decrease the risk for stricture occurrence postoperatively but is associated with higher rates of hemorrhage.17 Stricture of the site is common, and obstruction often recurs within 1 to 2 months of surgery.18 Location of the initial surgical site may prevent more proximal revision. This procedure is not a surgical option for animals who must retain the ability to reproduce.
Bladder Marsupialization and Vesicopreputial Anastomosis
These surgeries may be performed on patients that have experienced repeated urinary obstructions and previously undergone surgical procedures. Both surgeries involve creating a stoma into the bladder that is secured to the abdominal wall. The stoma is created through the abdominal wall on the ventral abdomen for a traditional bladder marsupialization. The stoma is created through the abdominal wall into the prepuce for a vesicopreputial anastomosis; the goal of this surgery is to decrease urine scalding. Both surgeries require significant follow-up care, as cystitis and urine scald are common complications, resulting from the animal no longer having control over urination and constantly draining urine from the marsupialization site.19
Prevention and Risk for Recurrence
Urolithiasis is a multifactorial problem with the potential for multiple underlying causes. The primary focus of prevention is ensuring adequate water intake and addressing dietary imbalances. A dietary calcium-to-phosphorus ratio of 2–3:1 is recommended to limit the absorption of magnesium and phosphorus, which predisposes the formation of struvite uroliths, and to avoid oversupplementation of calcium, which predisposes the formation of calcium-containing uroliths.3,20
Delaying castration of males until 6 months of age to ensure maximum urethral growth has been suggested, although this may not be achievable depending on the intended use of the animal. In addition, delayed castration does not guarantee the prevention of obstruction considering intact males have been shown to develop obstructions.
Some animals will develop uroliths with no definitive predisposing factors.21 Studies have shown that 20% to 55% of postoperative patients will experience complications, and the most common complication is reobstruction.22,23 In a study from 2021, the mean time to the first postoperative complication was approximately 6 months.22 Clients must understand this risk and know that surgery and follow-up care can be expensive and time-consuming. Surgery or dissolution and removal of uroliths is not considered a cure, merely a treatment for the immediate obstruction. A guarded or poor prognosis is associated with repeated obstructions, large number of uroliths in the urethra, and persistent azotemia postobstruction as well as rupture of the urethra, bladder, or kidney. Euthanasia is an appropriate and humane option for these patients.
Summary
Obstructive urolithiasis is a common emergency for small ruminants. Diagnosis involves the collection of a thorough history including potential risk factors; performing a complete physical examination; and diagnostics such as ultrasonography, radiography, and bloodwork. Prognosis and outcome depend on the type and location of urolith and presence of additional complications. Treatment often includes a combination of medical management and surgical procedures; however, recurrence of obstruction is common.
The post Diagnosis and Management of Obstructive Urolithiasis in Small Ruminants appeared first on Today's Veterinary Practice.
Discussion
Sign in to join the discussion.